

Admissions, boarding and going home
The Emergency Department model does not simulate your inpatient units. It holds no ward. An admitted patient waits in the ED for a bed from a bed board, which copies how a hospital hands beds to the ED, and leaves the model as Admitted when the patient leaves the ED. This article covers the bed board, the three care models in the group ADMISSION, DISCHARGE AND HOSPITAL SERVICES, going home, and where the report shows each.
Patients go home or wait for a bed
Section titled “Patients go home or wait for a bed”The Discharge / Admit tile reads “Patients go home, or wait in the ED for a bed from the bed board, then leave.” Its line on the face reads “Boarders wait on the bed board.”
The bed board
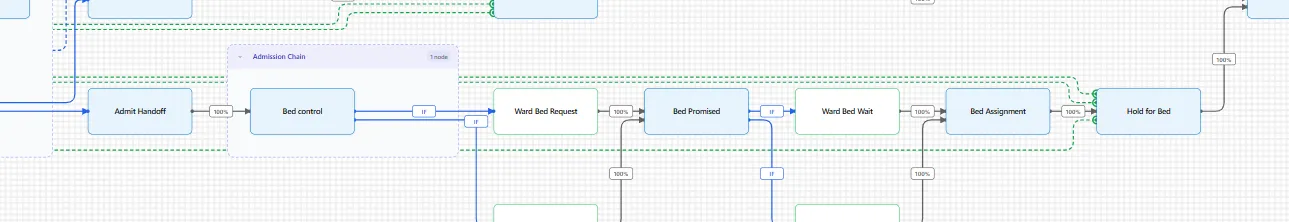
Section titled “The bed board”At the step Admit Handoff, an admitted patient is drawn a ward or an ICU bed by acuity. The chance of an ICU bed is 66.8 percent for ESI 1, 27.8 percent for ESI 2, 8.9 percent for ESI 3 and 1.1 percent for ESI 4 and 5. Then the patient:
- Waits in Ward Bed Request or ICU Bed Request until Bed Promised. The sicker patient is promised a bed first, and a promised bed is kept for its patient.
- Waits in Ward Bed Wait or ICU Bed Wait until the bed opens.
- Goes through Bed Assignment, which takes 5 to 30 minutes, most often 15.
- Boards on through Hold for Bed: the admitting orders still owed, then the nurse report, T(10, 15, 25) minutes, and the transport, T(15, 30, 60) minutes.
The patient keeps the ED space, the nurse and the provider until Hold for Bed ends.
The board itself has steps of its own. A Bed Huddle promises and pulls beds at 07:00 and 14:00, and gives some back at 19:00. Ward Bed Opens and ICU Bed Opens open each bed at its time. The patient types Huddle and Bed Opening carry them. The report never lists the bed board’s own steps under Time by care step, and the ED cost never counts them, because the board is the hospital’s and the ED counts no inpatient cost.
Diversion reads the board too. Its trigger is the bed board’s count of admitted patients still in the ED. See Care models.
Admission Chain
Section titled “Admission Chain”“After the admit decision: bed control, the orders still owed, the nurse report and the transport, all while boarding.” The face line reads “From the admit decision to the ward.” It is marked Possible from 20,000 visits and Suited from 50,000.
After Admit Handoff, bed control takes the request and the bed board finds a bed. The patient waits on the board for the bed, then in Hold for Bed for the hospitalist’s orders if they are not written yet, then for the nurse report and the transport. Boarding runs through all of it, and the patient keeps the ED space and the nurse.
An admitted stay takes about 10 minutes of bed control, the orders still owed of a wait of about 75 minutes from the bed request, a 15 minute report and a 30 minute transport. That is about two hours in all when a bed is open. With Holding orders on, a medical-surgical or telemetry admit owes no orders wait, and the ED provider spends a few minutes writing them, by acuity. The care model adds no space, staff or cost.
In a scenario the boxes are Bed control, minutes, Admission orders, minutes, Holding orders, 1 on and Holding orders time, percent.
Early Bed Request
Section titled “Early Bed Request”“After the exam, a likely admit has the ward bed asked for at once, so bed control overlaps the workup.” The face line reads “Ask for the bed at the exam.” Early Bed Request needs Admission Chain. It is marked Possible from 20,000 visits and Suited from 40,000.
After the exam, a patient at ESI 1 to 3 whom the provider thinks will likely be admitted has the ward bed asked for at once. About 28 percent of such patients are flagged to start with. If the patient is admitted, bed control takes only what is left of its minutes, which saves up to about 10 minutes. A patient who goes home after all leaves the early ask unused. The boarding clock still starts at the admit order.
In a scenario the boxes are Flagged up to ESI, Admits flagged, percent and False flags, percent. A kind of step, Likely-admit request, marks the request, and Bed promised marks the bed board’s promise.
Transfer Out
Section titled “Transfer Out”“A patient another hospital must take waits in the ED space for acceptance and the ambulance, then leaves.” The face line reads “Sent on to another hospital.” It is marked from any size. The patients it moves are 2.4 percent of visits overall, 5.6 percent of visits under 20,000 a year and 1.0 percent at high volume.
After the decision, a patient who is not admitted and whom another hospital must take waits in the ED space for acceptance, about an hour, then for the ambulance, about half an hour, then for departure, about 26 minutes. The patient leaves as Transferred out. The provider is free once the patient is accepted, and the nurse stays until the patient leaves. Each transfer’s ambulance is on the admission line of the cost: see Cost per patient.
In a scenario the boxes are Transferred, percent not admitted, Acceptance, minutes, Ambulance, minutes and Departure, minutes.
Going home
Section titled “Going home”A patient who goes home has two steps. Discharge with the nurse takes T(45, 60, 80) minutes, for the nurse’s instructions and teaching. Discharge takes T(30, 45, 60) minutes, for the paperwork and the ride. The bed, chair or room is held until the patient leaves, then cleaned. See Cleaning beds, chairs and rooms.
On the Getting Out tab
Section titled “On the Getting Out tab”The Getting Out tab of the report shows what the patients here waited for. Boarding times how long admitted patients are held, Bed request to assigned times the wait for a bed, Boarding pending transfer times how long patients sent to another hospital wait after the decision, and Likely admit to order times how long it takes from an early bed request to the admit order. See The emergency department report tabs.
Where to read more
Section titled “Where to read more”- The Emergency Department palette: the Discharge / Admit tile and the step times by acuity.
- Care models: the marks and boxes of all nineteen.
- Start a typical emergency department: the Inputs table and its row for the bed board.
- The emergency department report tabs: Getting Out.
- Cost per patient: what the cost counts and what it leaves to the hospital.